The long-term breast cancer findings from the Women’s Health Initiative (WHI) are not a single verdict on estrogen. In women with a previous hysterectomy, assignment to conjugated equine estrogen alone was associated with fewer breast cancer diagnoses and fewer breast cancer deaths than placebo. In a separate population with a uterus, assignment to that estrogen plus medroxyprogesterone acetate was associated with more diagnoses, without a statistically significant difference in breast cancer mortality.
Those findings came from follow-up extending beyond 20 years, not from 20 years of assigned medication. They also did not come from a head-to-head comparison of estrogen alone against combined treatment. This analysis uses the indexed primary report abstracts for WHI and ELITE, together with available official prescribing information and FDA material; it does not represent a review of all trial protocols, supplements, or full research articles.
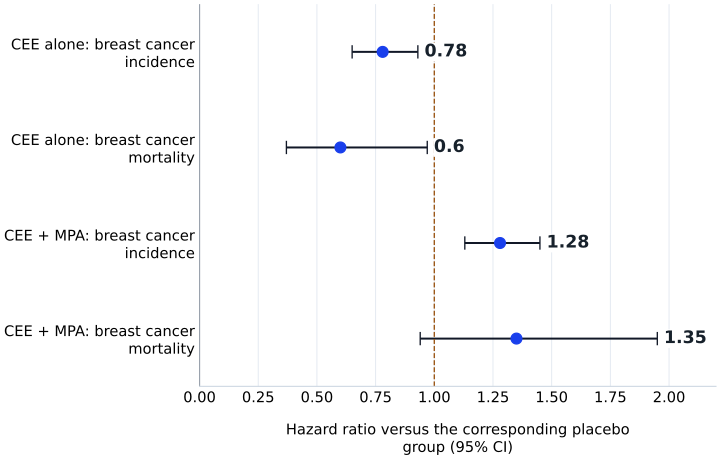
WHI randomized 10,739 women with prior hysterectomy in the estrogen-alone trial and 16,608 women with a uterus in the estrogen-plus-progestin trial.
Study facts at a glance
Two distinct populations: WHI randomized 10,739 women with prior hysterectomy in the estrogen-alone trial and 16,608 women with a uterus in the estrogen-plus-progestin trial. Source 1
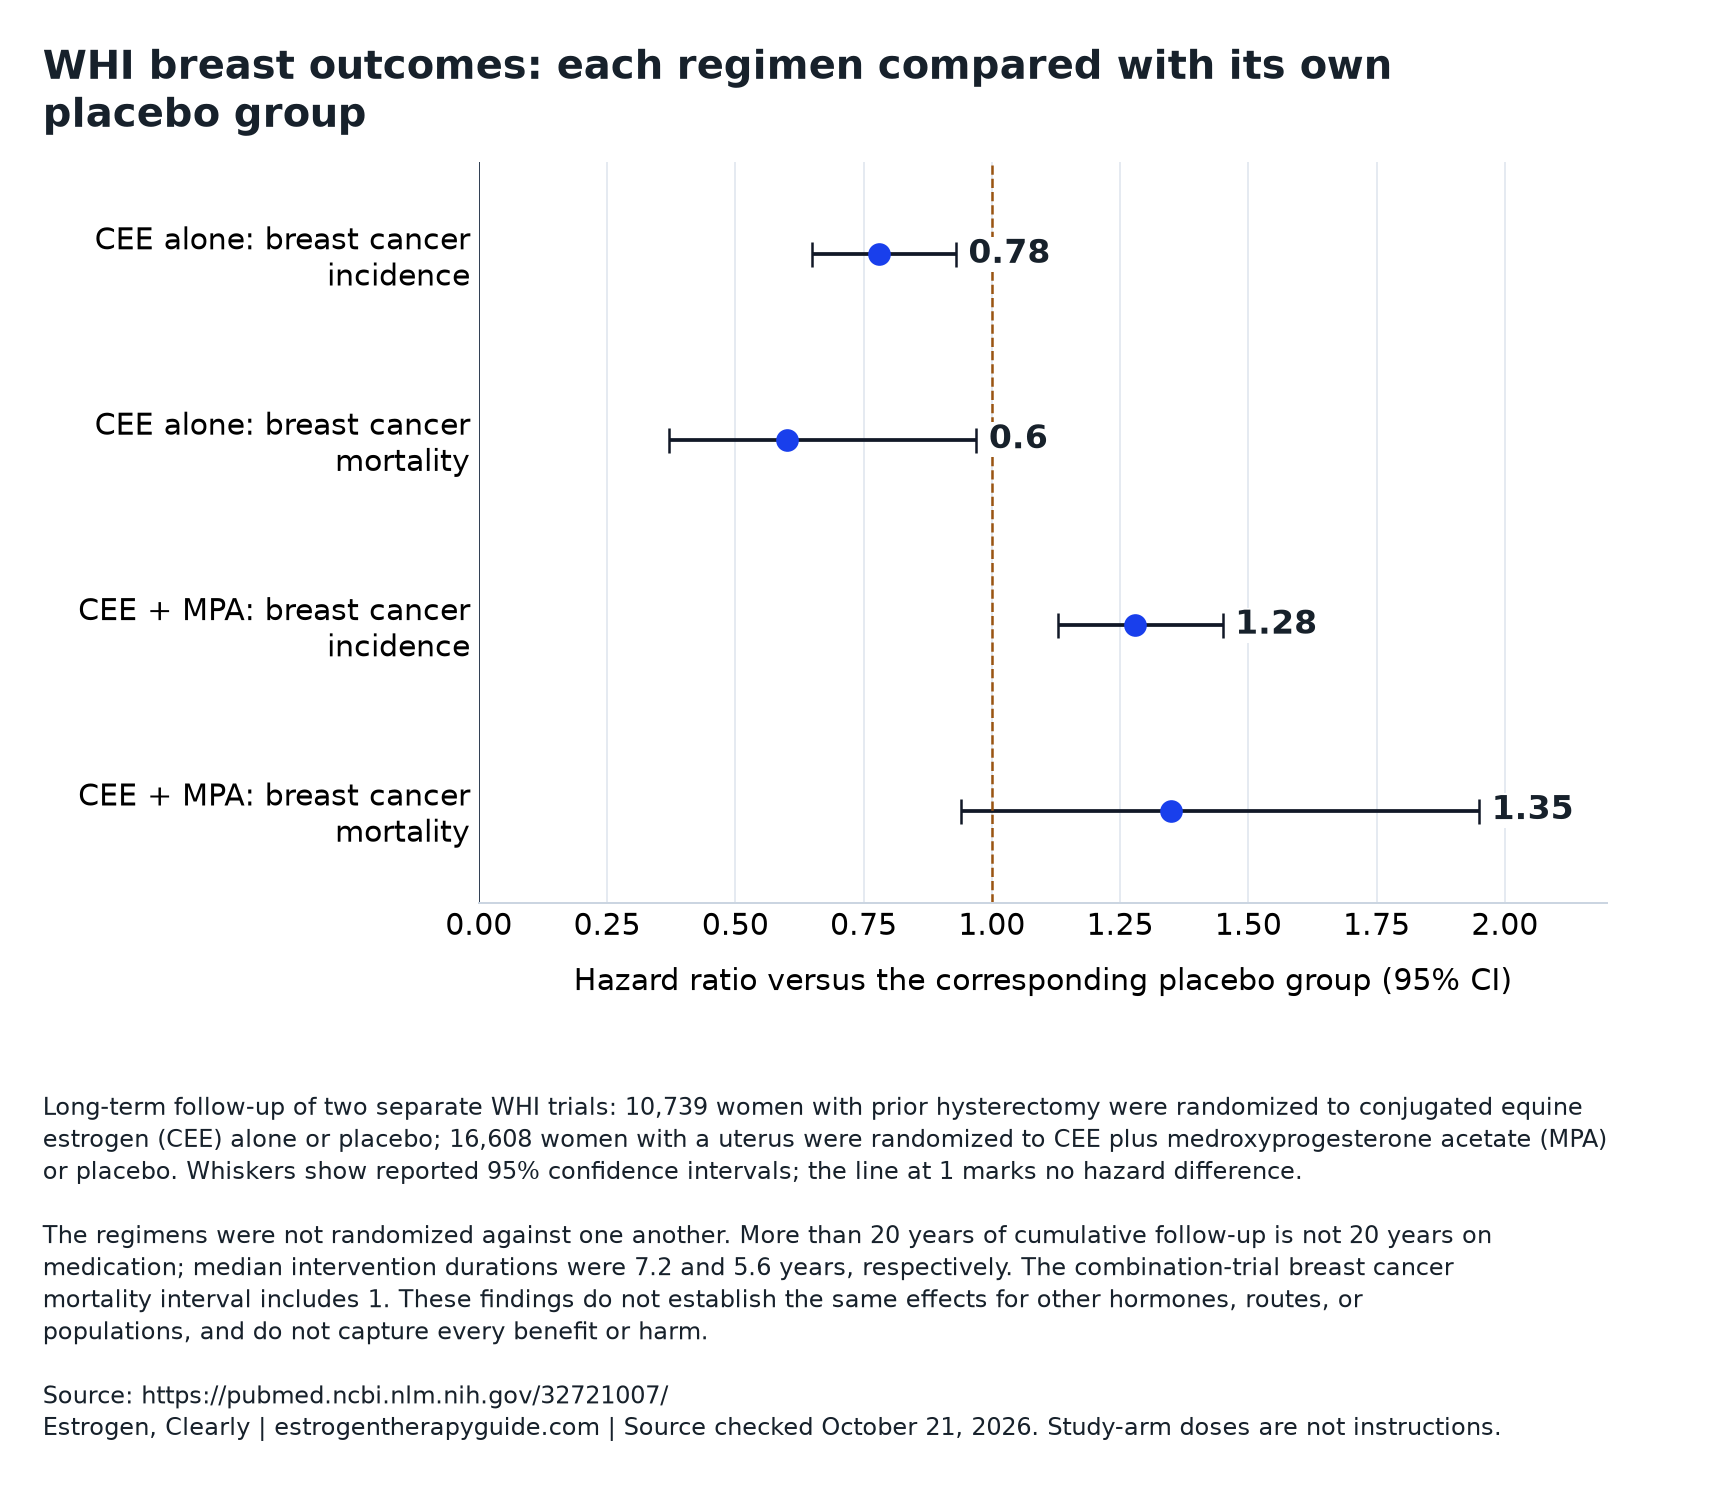
Estrogen-alone incidence: CEE alone versus placebo: 238 versus 296 breast cancers; hazard ratio 0.78, 95% confidence interval 0.65–0.93. Source 1
Combined-treatment incidence: CEE plus MPA versus placebo: 584 versus 447 breast cancers; hazard ratio 1.28, 95% confidence interval 1.13–1.45. Source 1
Breast cancer mortality: The hazard ratio was 0.60 with CEE alone and 1.35 with CEE plus MPA. Only the estrogen-alone mortality comparison reached statistical significance. Source 1
Label changes are product-specific: FDA announced approved warning changes for an initial six products in February 2026. Remaining warnings and contraindications still require checking the exact product label. Source 4 Source 2
Uterine history determined which trial a woman could enter
The two placebo-controlled randomized trials enrolled 27,347 postmenopausal women at 40 US centers between 1993 and 1998. Participants were 50 through 79 years old, with a combined baseline mean age of 63.4 years and a standard deviation of 7.2 years. They had no prior breast cancer and had a negative screening mammogram at entry. These eligibility details matter: this was not a trial of treatment after breast cancer.
Among women with prior hysterectomy, 5,310 were assigned CEE alone and 5,429 placebo. Among women with a uterus, 8,506 were assigned CEE plus MPA and 8,102 placebo. Randomization supports the treatment-versus-placebo comparison inside each population. It does not make the two populations interchangeable.
Uterine status is therefore part of the evidence, not an incidental demographic detail. The guide to estrogen and progesterone provides a broader framework for reading the complete prescription. For WHI specifically, the valid comparisons remain CEE versus its placebo and CEE plus MPA versus its separate placebo.
The two randomized WHI comparisons—not a three-arm trial
| Design feature | Prior hysterectomy | Uterus present |
|---|---|---|
| Total participants | 10,739 | 16,608 |
| Assigned active treatment | Oral CEE 0.625 mg daily | Oral CEE 0.625 mg plus MPA 2.5 mg daily |
| Active / placebo allocation | 5,310 / 5,429 | 8,506 / 8,102 |
| Median intervention duration | 7.2 years | 5.6 years |
Read the underlying chart data: download CSV or download the source-labeled chart.
Long follow-up is different from prolonged assigned treatment
The combination trial stopped its intervention in 2002 after a median 5.6 years; the estrogen-alone intervention stopped in 2004 after a median 7.2 years. The breast outcomes report followed participants through December 31, 2017, describing more than 20 years of median cumulative follow-up. Its central question concerned the long-term outcomes associated with prior randomized treatment.
That distinction changes the meaning of every estimate. The results combine time during the assigned intervention with later observation. They do not estimate what would happen if every participant continuously used the original medication for two decades. Nor can the abstract establish the breast cancer effect of any particular later pattern of hormone use.
Mortality information was available for more than 98% of participants. That is an important strength for tracking deaths, but it is not a claim that 98% adhered to treatment. High outcome ascertainment and sustained medication adherence answer different methodological questions; confusing them would make the trial sound more like a continuous-exposure experiment than it was.
CEE alone showed lower incidence within the hysterectomy population
In the estrogen-alone trial, investigators reported 238 breast cancers among women assigned CEE and 296 among those assigned placebo. Annualized incidence rates were 0.30% and 0.37%, respectively. The hazard ratio was 0.78, with a 95% confidence interval of 0.65–0.93. The interval excluded 1, supporting a statistically significant difference.
A hazard ratio compares the rate at which events occur over follow-up, accounting for event timing. Here, 0.78 corresponds to an estimated 22% lower hazard—not a 22-percentage-point reduction in a woman’s probability of developing breast cancer. The confidence interval corresponds to estimates ranging from roughly 7% to 35% lower hazard.
The annualized rate difference was 0.07 percentage points, or about seven fewer diagnoses per 10,000 person-years. That translation helps show scale, but it is not a cumulative 20-year benefit. It also does not establish CEE as a breast cancer prevention prescription. The observed benefit belongs to this regimen, comparator, population, and follow-up structure.
CEE plus MPA showed higher incidence in women with a uterus
The combined-treatment trial recorded 584 breast cancers with CEE plus MPA and 447 with placebo. Annualized rates were 0.45% versus 0.36%. The hazard ratio was 1.28, with a 95% confidence interval of 1.13–1.45: an estimated 28% higher hazard, with the interval spanning approximately 13% to 45% higher hazard.
Subtracting the annualized rates gives 0.09 percentage points, equivalent to about nine additional diagnoses per 10,000 person-years. This is a rate-based description, not a statement that nine additional women out of every 10,000 treated will develop cancer over any chosen treatment period. Time and the population denominator remain essential.
The contrast with estrogen alone is scientifically important, but it does not isolate MPA as the sole explanation. Women were not randomized between CEE alone and CEE plus MPA within one common population. The results establish two different treatment-versus-placebo findings, leaving the contributions of formulation, uterine history, and other population differences incompletely separated.
Long-term breast endpoints: each active regimen compared with its own placebo
| Endpoint | CEE alone / placebo | CEE plus MPA / placebo |
|---|---|---|
| Breast cancer diagnoses | 238 / 296 | 584 / 447 |
| Annualized incidence | 0.30% / 0.37% | 0.45% / 0.36% |
| Incidence hazard ratio, 95% CI | 0.78, 0.65–0.93 | 1.28, 1.13–1.45 |
| Breast cancer deaths | 30 / 46 | 71 / 53 |
| Annualized breast cancer mortality | 0.031% / 0.046% | 0.045% / 0.035% |
| Mortality hazard ratio, 95% CI | 0.60, 0.37–0.97 | 1.35, 0.94–1.95 |
Mortality provides a separate, less precise answer
Breast cancer incidence was the primary endpoint in this report and a protocol-prespecified primary monitoring outcome for harm. Death from breast cancer and death after breast cancer were secondary outcomes. Those latter concepts differ: a death following a diagnosis is not necessarily a death caused by that cancer. The numerical mortality comparisons here concern breast cancer deaths.
CEE alone was associated with 30 breast cancer deaths versus 46 with placebo. Annualized mortality was 0.031% versus 0.046%; the hazard ratio was 0.60, with a 95% confidence interval of 0.37–0.97. This was statistically significant, but the relatively small death counts produced considerably more uncertainty than the incidence estimate.
With CEE plus MPA, there were 71 breast cancer deaths versus 53, and annualized rates of 0.045% versus 0.035%. The hazard ratio of 1.35 had a confidence interval of 0.94–1.95. That interval includes no difference, a modest reduction, and a substantial increase. Calling this proof of no mortality effect would discard the uncertainty the interval explicitly describes.
Counts, annualized rates, and hazards answer different questions
Counts describe how many events were recorded. Annualized rates relate events to accumulated observation time. Hazard ratios incorporate the timing of events in a comparative analysis. These are complementary summaries, not interchangeable ways of writing the same probability. Unequal group sizes and observation time make raw event counts especially unsuitable as equal-follow-up risk estimates.
For example, the estrogen-alone mortality rate difference is 0.015 percentage points per year, or about 1.5 deaths per 10,000 person-years. That is the arithmetic difference between the published annualized rates. It is not an individualized forecast, and multiplying it by 20 would impose a constant-rate assumption that the abstract does not establish.
Likewise, an incidence hazard ratio of 0.78 is not a cumulative risk ratio of 0.78 at every follow-up date. Without the necessary time-specific risk estimates, these summaries should not be turned into a number needed to treat or harm. The useful public-facing interpretation is the direction, approximate relative magnitude, absolute rate scale, and uncertainty together.
WHI did not test every estrogen or progesterone formulation
The studied estrogen was oral conjugated equine estrogen, not estradiol. The combination regimen used medroxyprogesterone acetate, not micronized progesterone. These names identify different treatments. A result for one cannot establish the exact breast cancer effect of another simply because both are described as menopausal hormone therapy.
The current BIJUVA prescribing information makes the evidence gap explicit: the relevance of WHI’s combined-regimen breast findings to other doses, routes, and estrogen–progestogen products is unknown. That uncertainty neither proves identical risk nor proves absence of risk. The patch-versus-pill guide and local-versus-systemic estrogen guide help keep these treatment categories separate.
BIJUVA itself is an oral estradiol-and-progesterone product indicated for moderate to severe menopausal vasomotor symptoms in women with a uterus. Its symptom-efficacy substudy evaluated 12-week outcomes, within a 52-week safety study. Such evidence answers a different question from WHI’s long-term breast outcomes. Neither those shorter studies nor WHI establish equivalent outcomes for compounded preparations or other formulations.
ELITE’s timing finding does not resolve the breast cancer question
The separate ELITE trial randomized 643 healthy postmenopausal women within groups defined by time since menopause: less than six years or at least ten years. It tested oral estradiol, with sequential vaginal progesterone for women with a uterus, against placebo. Its primary endpoint was change in carotid-artery wall thickness, an imaging measure of subclinical atherosclerosis—not breast cancer.
Over a median five years, early-postmenopause participants had mean thickness progression of 0.0044 mm per year with estradiol versus 0.0078 with placebo. The corresponding late-postmenopause rates were 0.0100 and 0.0088 mm per year. The treatment-by-timing interaction was statistically significant, but cardiac CT measures did not differ significantly in either timing group.
Our ELITE timing-trial analysis examines that distinction. An arterial imaging result cannot establish fewer breast cancers, heart attacks, or deaths. ELITE was funded by the National Institute on Aging; the accessible WHI breast abstract does not identify sponsorship. Neither report supplies a randomized answer to every modern hormone regimen used near menopause.
Revised warnings coexist with documented adverse outcomes
On February 12, 2026, FDA announced approved labeling changes for an initial six menopausal hormone products, removing cardiovascular disease, breast cancer, and probable dementia statements from their boxed warnings. This did not establish that every marketed label had changed. Nor does changing the prominence or wording of a warning reverse the events recorded in randomized trials.
The updated BIJUVA label retains cardiovascular and malignancy warnings and contraindications including breast cancer or its history, certain clotting or arterial disease histories, and liver disease. Its WHI discussion reports higher hazards of stroke, 1.37 (95% CI 1.07–1.76), and pulmonary embolism, 1.98 (1.36–2.87), during the combined-regimen intervention period. These are not estimates from the long-term breast analysis.
Product-specific adverse effects also matter. In BIJUVA’s one-year safety study, breast tenderness occurred in 4.0% of 424 women receiving estradiol/progesterone 0.5 mg/100 mg and 10.4% of 415 receiving 1 mg/100 mg, versus 0.7% of 151 receiving placebo. Headache, nausea, and vaginal bleeding were also reported. Those findings should remain attached to their own product and study rather than being pooled informally with WHI.
Evaluating a treatment claim requires an evidence match
A useful reading sequence is to identify the population, exact hormones, route, comparator, duration, and endpoint before accepting a claim. A statement about symptom relief does not establish cancer prevention. A favorable breast endpoint does not establish an overall health benefit. Conversely, an adverse finding for CEE plus MPA does not quantify the effect of every other combination.
Editorial interpretation: purchasing or care arrangements add a separate documentary question, not another clinical endpoint. Readers comparing services can use the Alloy review or Midi review to check documented fees, appointment terms, and medication arrangements. Those reviews do not establish access to the studied products, condition-specific care, or WHI-like outcomes.
The questions-before-starting-estrogen guide can help organize a consultation around the actual proposed treatment. Scientifically, important gaps remain: how long-term breast outcomes differ across modern formulations, what treatment duration changes, and how well estimates apply to women beginning closer to menopause. These WHI comparisons are strong evidence for their assigned regimens, not a complete map of hormone therapy.
Questions about the evidence
Did WHI directly compare estrogen alone with estrogen plus progestin?
No. Women with prior hysterectomy entered the CEE-alone versus placebo trial; women with a uterus entered the CEE-plus-MPA versus placebo trial. Randomization protects each within-trial comparison. It does not support treating the difference between the two active regimens as a head-to-head estimate or as proof that one ingredient alone caused the divergent results.
Does the estrogen-alone result mean estrogen prevents breast cancer?
The narrower conclusion is that prior assignment to oral CEE was associated with lower incidence and breast cancer mortality than placebo in this hysterectomy population. That is meaningful randomized evidence, but it does not establish a prevention indication or the same effect for estradiol, patches, local vaginal products, or women with a uterus.
Why was higher combination-treatment mortality not statistically significant?
The estimate was imprecise: its 95% confidence interval, 0.94–1.95, crossed 1. Breast cancer deaths were much less frequent than diagnoses, leaving less information for estimating the mortality effect. The result therefore leaves a substantial increase possible; it does not demonstrate equal mortality or cancel the statistically significant increase in incidence.
Were participants taking the assigned hormones for more than 20 years?
No. Median assigned-intervention durations were 7.2 years for CEE alone and 5.6 years for CEE plus MPA. More than 20 years described cumulative follow-up. The later outcomes inform the consequences associated with prior randomized use, not uninterrupted use of the original regimen throughout the entire observation period.
Do the 2026 FDA changes mean breast cancer warnings no longer matter?
No. FDA’s initial announcement covered six products, and product labels must be checked individually. BIJUVA’s updated information still includes malignancy precautions and contraindicates use with breast cancer or a history of breast cancer. A boxed-warning revision changes regulatory communication; it does not supply new randomized evidence that all hormone formulations have no breast cancer risk.
What this evidence supports
WHI’s long-term breast findings are most informative when their boundaries remain visible. CEE alone reduced breast cancer incidence and mortality relative to placebo in women with prior hysterectomy. CEE plus MPA increased incidence in women with a uterus, while its mortality estimate remained uncertain. These are different randomized comparisons, not contradictory answers to one universal hormone question. Their lasting value is the combination of randomized assignment, long observation, and endpoint-specific reporting. Their principal limitation for present-day claims is the distance between the exact regimens studied and the broader range of products, populations, and treatment patterns now discussed.
Research access and limitations
WHI and ELITE numerical analyses here rely on indexed primary abstracts, not complete protocols or supplements. Official BIJUVA prescribing information supplies separately identified safety and product context; the FDA announcement supplies regulatory context. Detailed adherence patterns, postintervention treatment trajectories, and additional subgroup estimates are not established by the accessible abstracts.
Sources & reading
Source check dates appear with each record below. Provider pages describe their own services; they do not establish clinical superiority.
- Association of Menopausal Hormone Therapy With Breast Cancer Incidence and Mortality During Long-term Follow-up of the Women's Health Initiative Randomized Clinical Trials. ↗Indexed primary study abstract · Checked 2026-10-21
- DailyMed: BIJUVA estradiol and progesterone capsule prescribing information ↗Full official prescribing information · Checked 2026-10-21
- Vascular Effects of Early versus Late Postmenopausal Treatment with Estradiol. ↗Indexed primary study abstract · Checked 2026-10-21
- FDA: February 12, 2026 approval of initial hormone-therapy label changes ↗Federal regulatory announcement · Checked 2026-10-21